for DBS
Subcortical visualization support
for deep brain stimulation planning.
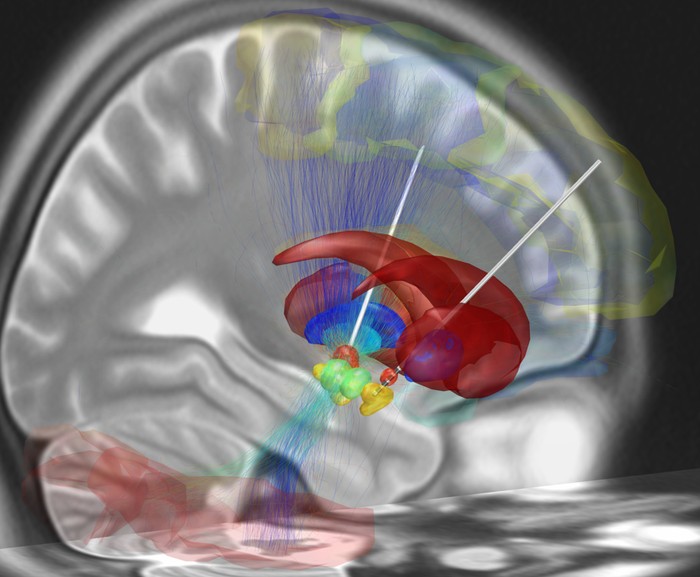
STAGE derives FGATIR gray/white matter contrast alongside iron-sensitive QSM and R2*/T2* maps from one acquisition — additional information for teams reviewing subcortical anatomy during planning.
STAGE supports visualization for planning. It does not perform targeting, and it does not diagnose or treat disease.
THE CLINICAL CHALLENGE
Subcortical targets are small, and conventional contrast is thin.
DBS planning depends on confident review of structures a few millimeters across — the STN, GPi, substantia nigra and the borders between them. On routine T1- and T2-weighted series those boundaries are faint, and their appearance shifts with scanner and protocol.
Low boundary contrast
STN and GPi borders are faint on standard series.
Protocol variability
Appearance differs scanner to scanner.
Atlas assumptions
Iron varies by patient and age, so teams lean on atlases.
WHAT STAGE DELIVERS
Two complementary outputs that show what conventional MRI leaves faint
Where conventional T1- and T2-weighted series render subcortical boundaries as low-contrast gray, STAGE outputs separate those structures on a different physical property — tissue relaxation and iron content. Read together, they give planning teams a clearer view of the STN, GPi and substantia nigra in the individual patient. Every output is reconstructed from a single STAGE acquisition, exported as a standard DICOM series, and intended to support visualization and measurement by qualified clinicians during planning review.
HEAD-TO-HEAD · SAME SUBJECT
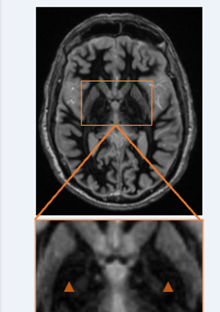
Conventional FGATIR fails to show GPi and lamina
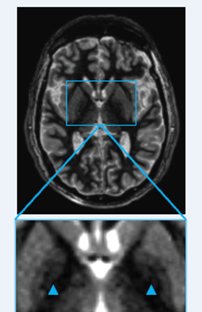
STAGE-FGATIR shows GPi and lamina
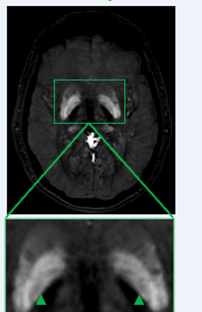
STAGE-QSM provides additional information
COMPUTED CONTRAST
FGATIR gray/white matter contrast
Computed from STAGE T1 and proton-density maps to sharpen the white matter borders that routine T1-weighted series blur — and with no separate inversion-recovery sequence to schedule.
QUANTITATIVE MAP
QSM — susceptibility in physical units
Iron-rich structures such as the STN, GPi and substantia nigra carry distinct susceptibility signatures that conventional contrast cannot separate — supporting visualization of the patient’s own anatomy rather than atlas assumptions.
WHO BENEFITS
Across the care continuum
Neurosurgeon
Better visualization of target structures supports pre-operative planning review.
More informed operative planning can support lead placement during surgery.
Supports the surgical team's own assessment of placement and revision risk.
Neurologist
Clearer placement review can support more effective lead programming.
Quantitative results support longitudinal assessment of key disease biomarkers.
Standardized outputs facilitate disease tracking across follow-up examinations.
Radiologist
Qualitative and quantitative MRI contrasts are automatically co-registered.
Often reduces the need for additional specialized MRI scans.
Enables image contrast adjustment after the scan to optimize review.
*Potential clinical applications reflect ongoing development and workflow evaluation and do not imply additional cleared indications.
WORKFLOW FIT
One acquisition. The scanners you already have.
STAGE runs as a single multi-echo sequence inside the existing planning protocol. Reconstruction is automated, and every output lands in PACS as a standard DICOM series alongside the rest of the exam.
Because the platform is vendor-agnostic across 1.5T and 3T, a center running a mixed fleet can standardize what planning review looks like — without replacing hardware.